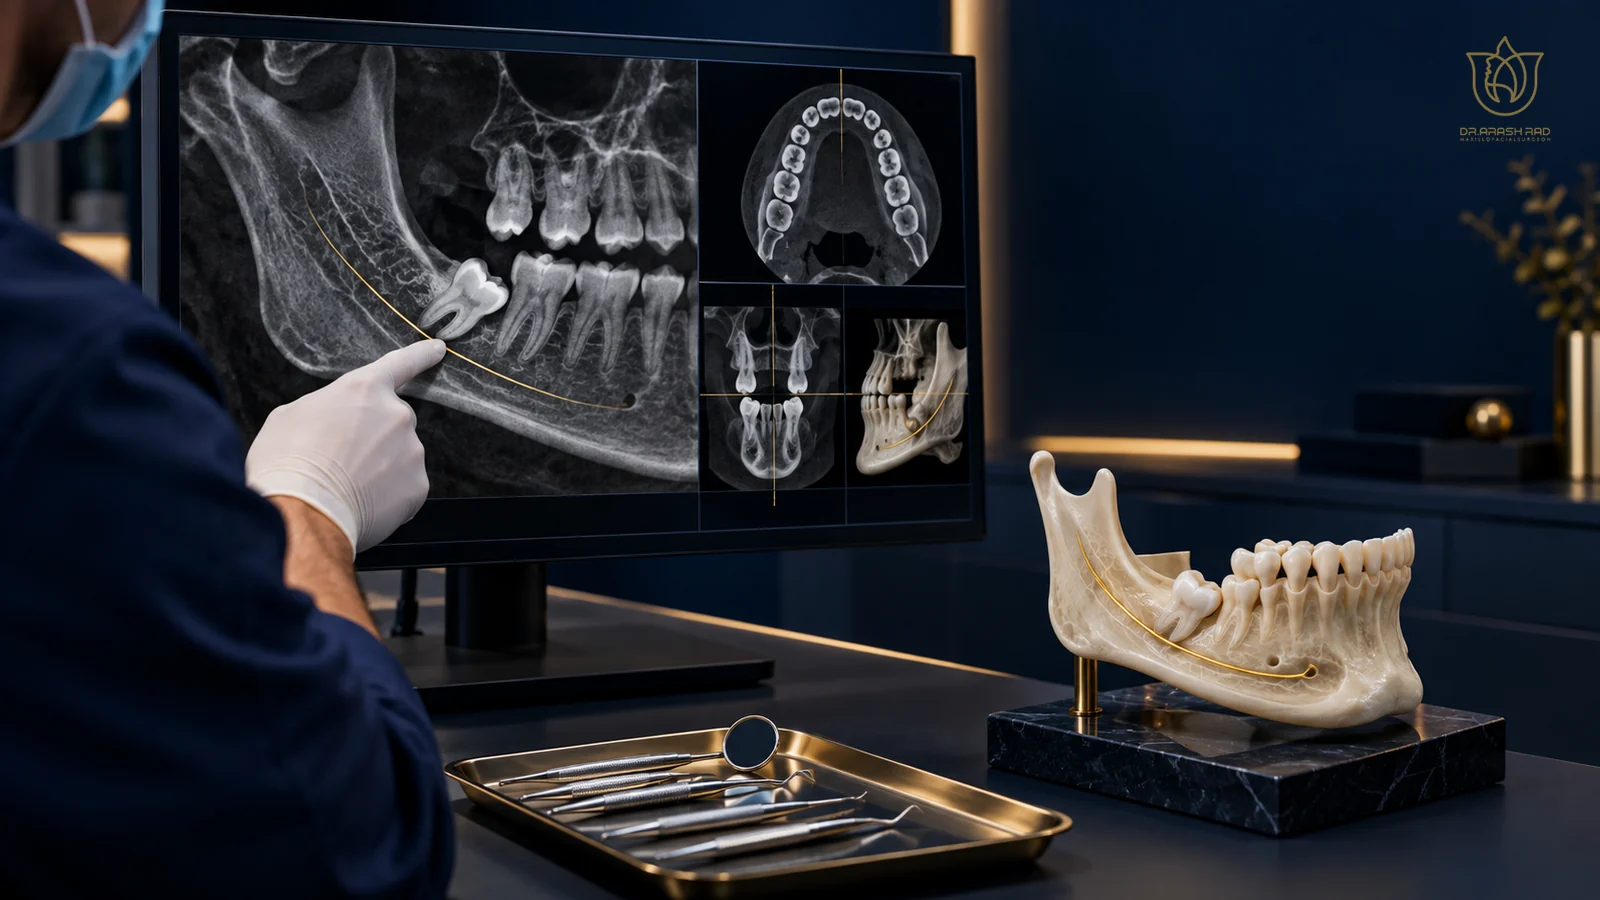
Oral and dental surgery: more than wisdom teeth
Oral surgery includes impacted teeth, difficult extractions, surgery that supports orthodontic treatment, implant placement and assessment or treatment of selected jaw cysts and soft-tissue lesions. Pain, swelling or a finding on an X-ray does not by itself identify the right procedure. The diagnosis comes first, followed by a discussion of monitoring, preserving the tooth, non-surgical care or surgery. The existing detailed guide to impacted teeth and recovery follows these additional sections.
An impacted canine does not always need removal
A canine that has not erupted as expected needs an assessment of position, available space, neighbouring roots and dental development. In selected cases, an oral surgeon exposes the crown and places an attachment so an orthodontist can guide the tooth gradually into position. This coordinated approach differs from extraction. Other situations may call for removal or an alternative plan. Bring previous radiographs and an orthodontic treatment plan if available. A mobile-phone photograph cannot establish which approach is suitable.
Dental implants: planning bone, gum and the future crown together
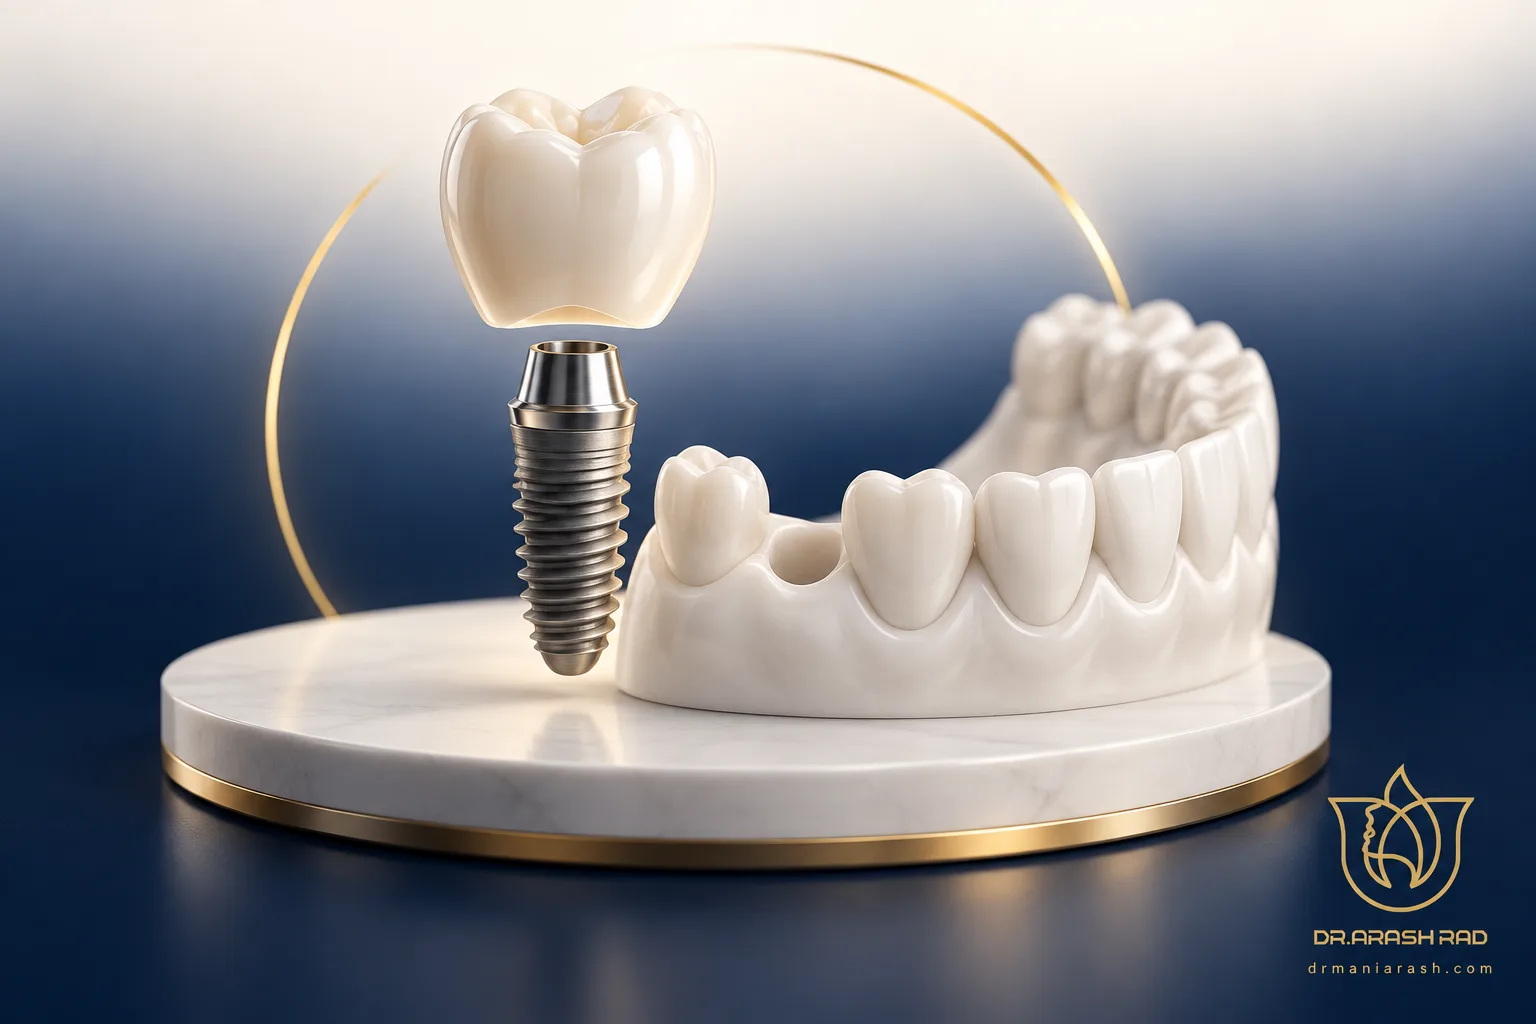
An implant is a support placed in bone for a replacement tooth, but treatment involves more than inserting a screw. Bone volume, gum health, neighbouring teeth, the opposing bite and proximity to nerves or the sinus must be considered. The future crown matters from the beginning: an implant position should support function, appearance and cleaning. A staged plan may be needed if infection must be addressed or tissues prepared first. Immediate placement or loading is not suitable for every patient.
Ask how many stages are expected, what temporary replacement is available and which findings could change the schedule. After restoration, the implant itself does not decay like a natural tooth, but surrounding tissues can become inflamed and lose support. Cleaning instruction, gum checks and review of the forces on the crown remain important. Report bleeding, swelling, pain, looseness or new food trapping. Brand name alone does not guarantee success; planning, treatment and maintenance all matter.
How are jaw cysts investigated?
Some jaw lesions are found incidentally on dental imaging and may initially cause no pain. Others are associated with swelling, tooth displacement, infection or altered sensation. A dark area on an X-ray is not automatically a confirmed cyst because several conditions can resemble each other. History, examination and imaging guide the next step, which may include further imaging or tissue sampling. The diagnosis, size, location and relationship to roots or nerves influence treatment and follow-up.
Options may include removal, a staged decompression approach or another method appropriate to the diagnosis. A related tooth may need separate consideration. Tissue examination can affect the follow-up plan and should not be dismissed once pain improves. A cyst and an abscess are not the same diagnosis. Antibiotics may be part of infection management where indicated, but do not necessarily remove an underlying lesion or its cause. Do not repeatedly self-prescribe based on a previous episode.
Soft-tissue surgery and biopsy inside the mouth
A persistent unexplained ulcer, lump or colour change may need examination and sometimes a biopsy. Duration, growth, discomfort, bleeding and local irritation help guide assessment. A biopsy is a way to clarify the diagnosis; it does not mean a particular disease has already been confirmed. Ask about wound care, when the result will be available and the appointment to discuss it. Rapidly increasing swelling, difficulty swallowing or breathing, or significant deterioration requires urgent care rather than waiting for a routine appointment.
For a consultation, bring your medicines list, previous images and dental treatment reports. Read more about exposure and bonding of impacted teeth at AAOMS and jaw cyst and tumour treatment at the University of Maryland.
What does oral surgery & impacted teeth address?
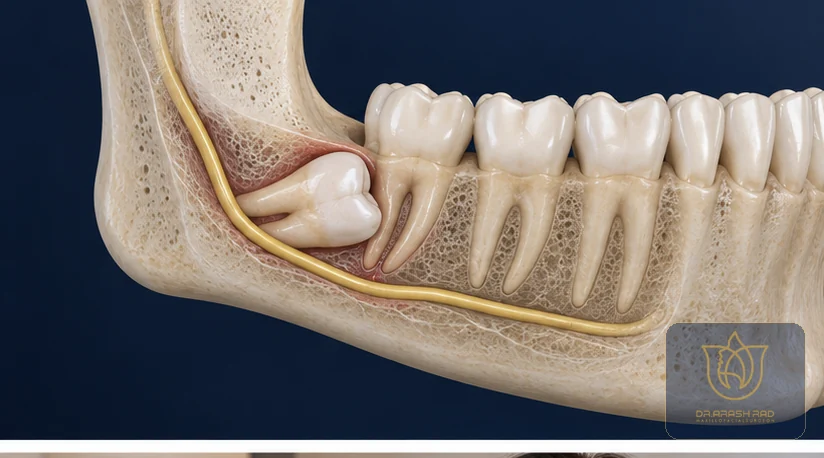
Oral surgery includes the assessment and treatment of impacted teeth, complex extractions, infections and selected lesions around teeth and jaw tissues. An impacted tooth has not erupted into the expected position, but the right response depends on symptoms, surrounding structures and the findings on examination and imaging.
Who might benefit from an assessment?
People may be referred for a wisdom tooth, a difficult extraction, repeated inflammation, a tooth close to a nerve or a lesion seen on an image. Not every impacted tooth needs to be removed immediately. The assessment weighs the risks of intervention against those of observation in the individual situation.
What is examined?
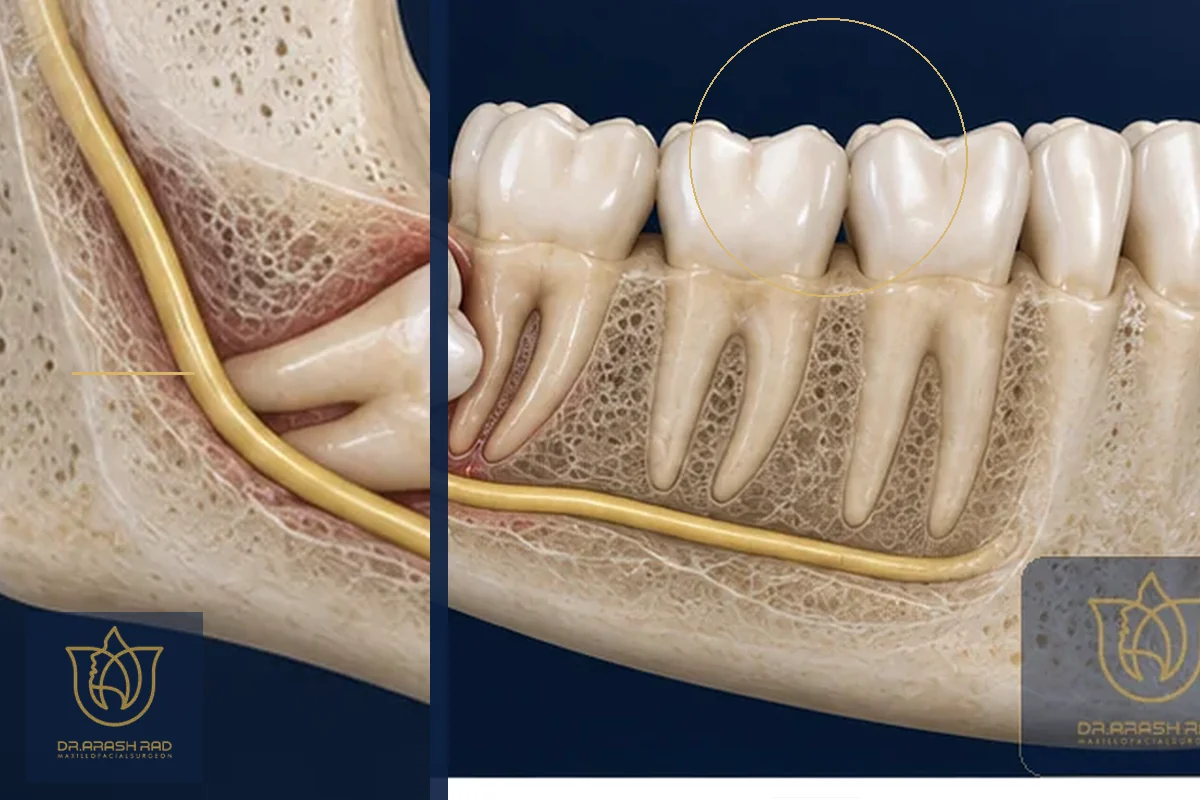
The surgeon reviews symptoms, the inside of the mouth, neighbouring teeth and the available radiographs. The position of roots, nearby nerves, the sinus and any surrounding change in bone may affect planning. Additional imaging is considered when it can clarify a question that matters to treatment or safety.
When a routine appointment should not wait
Some symptoms need prompt assessment rather than an ordinary appointment. These include rapidly increasing swelling, uncontrolled bleeding, fever with worsening oral symptoms, difficulty breathing or swallowing, and a new problem with sensation or closing the mouth after an injury. Breathing difficulty or severe bleeding requires emergency care. A routine online booking should not delay getting help.
Many questions about appearance and elective surgery are not emergencies. Taking time to understand a proposal is part of making a sound decision. If you are planning around a wedding, examination period or travel date, leave room for healing and follow-up. A personal deadline cannot reliably determine how quickly swelling will settle or when a result is ready to judge.
Making the most of your consultation
Start with the concern that matters most to you. Explain when it began, whether it affects daily life and what change you hope treatment will achieve. Previous treatment, symptoms that come and go, and anything that makes the problem better or worse can be relevant. A short written note often makes the conversation easier than trying to remember every detail at the appointment.
Photographs can help explain an aesthetic preference, but copying another person’s face is not a realistic treatment goal. Ask which features of your own anatomy support the proposed change and which place limits on it. If an explanation is unclear, ask to see it on an image or model. You should understand the reasoning well enough to describe the main options in your own words.
Why your medical history matters
Blood pressure problems, diabetes, heart or lung disease, bleeding conditions, medicine allergies, pregnancy, sleep apnoea, previous operations and a difficult anaesthetic experience can change the plan. Tell the team about prescribed medicines, non-prescription products, supplements and nicotine use. A medicine that seems unrelated to the face can still affect surgery or healing.
Do not stop or change a prescribed medicine on your own. Decisions about blood-thinning medicines or other regular treatment may require coordination with the clinician who prescribed them. Bring an up-to-date list and mention any new illness or medicine before the procedure. Accurate information helps the team decide whether further assessment or a change in timing is needed.
Imaging and digital planning
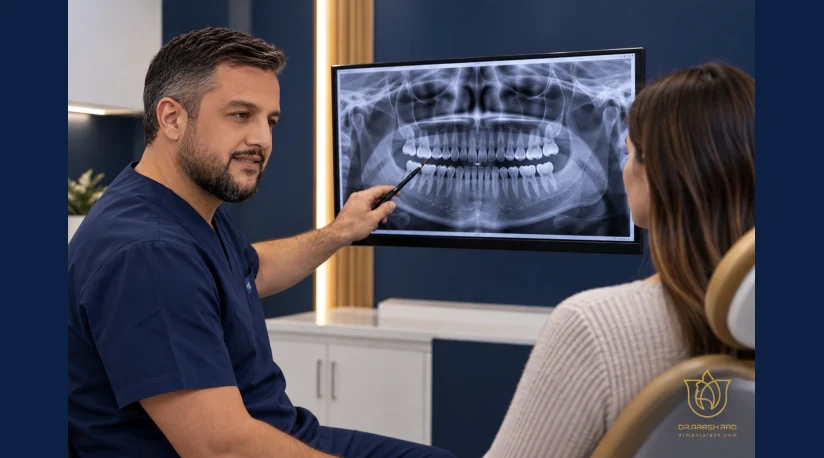
The type of image should answer a clinical question. An ordinary radiograph may provide enough information in one situation, while a CT scan or three-dimensional study is useful in another. Imaging may clarify the position of nerves, the thickness of bone, tooth roots, sinus anatomy or the relationship of the jaws. More imaging is not automatically better if it does not change a decision.
Digital models can support measurement and planning. Some procedures use a cutting guide, splint or custom component. These tools assist the surgeon, but the body is not a fixed computer model. Swelling, bone healing, skin behaviour and natural differences between the two sides of the face affect the result. A simulation helps communicate a goal; it is not a promise of an exact outcome.
Understand the diagnosis before choosing a technique
It is common to arrive with the name of a procedure in mind. The diagnosis still needs to come first. Similar appearances may have different causes, and an operation aimed at the wrong structure may make little difference or create an imbalance. Sometimes a smaller treatment is enough; sometimes a broader problem involving the bite or other structures needs attention.
A useful plan explains the main objective, the structures that will change, what is unlikely to change and the alternatives. It should also explain what may happen without treatment. Ask why a particular option is recommended over another. Complexity does not automatically mean quality, and a less invasive approach does not always provide the change a person needs.
Treatment options and alternatives
Depending on the diagnosis, options may include observation, treatment of infection, extraction, another surgical approach or referral for related care. If a tooth is close to a nerve, ask how that relationship influences the options. A technique’s name alone does not tell you whether it is appropriate or whether it avoids all risk.
Preparing in the weeks before surgery
Once a plan is agreed, the team provides instructions about tests, imaging, other consultations and medicines. Think practically about the early recovery period: help at home, suitable food, transport and time away from work or study. Arrange these around the advice for your operation rather than a generic timeline. Buying additional medicines or expensive recovery equipment without a recommendation is usually unnecessary.
Smoking, vaping, shisha and other nicotine exposure may interfere with healing. Discuss what changes are needed and when with the treating team. If you develop a cold, fever or another illness, tell the clinic before attending. Follow the centre’s fasting instructions precisely. Do not assume that fasting for longer or having a small snack outside the instructions is harmless.
What happens on the day of surgery
Before a procedure begins, the team checks identity, the planned operation, relevant allergies and fasting status. Local anaesthesia, sedation or general anaesthesia is selected according to the procedure and the person’s health. This is a chance to clarify remaining important questions, but unplanned last-minute changes should not be added without proper assessment and discussion.
The time spent at the treatment centre is longer than the operation itself. Admission, preparation, recovery and the checks needed for safe discharge all take time. Some operations require a hospital stay. After the procedure, staff assess breathing, pain, bleeding, nausea and general condition. Wait for permission before taking your own medicines, food or drinks.
How the procedure is planned
The procedure and anaesthesia depend on the tooth or lesion and the complexity of access. The surgeon explains the planned approach, how the wound will be managed and what to expect afterwards. For tissue sampling, ask how and when the findings will be discussed and whether they could change the next step.
The first days at home
Experiences differ even after procedures with the same name. Swelling, bruising, tightness, tiredness or reduced appetite can occur. The aim is not to endure every symptom without help: follow the prescribed care and contact the team if the course differs from what they explained. Discharge instructions should say what is expected and which changes need attention.
Keep a simple record of medicine times, fluid intake and questions. Rest is important, but prolonged immobility should not be assumed necessary unless you have been told so. Head position, compresses, bathing and activity restrictions vary between operations. A daily photograph is useful only when requested for follow-up; changes in angle or lighting can create unnecessary worry.
Recovery after oral surgery & impacted teeth
Eating, mouth care and activity instructions are tailored to the wound. Swelling, soreness and temporary difficulty opening the mouth may occur. Follow the specific advice on cleaning and rinsing rather than applying a general internet routine to a fresh surgical site.
Pain, swelling and bruising
Pain should be manageable with the prescribed plan. New, severe or increasing pain, particularly with fever, discharge, a bad smell or worsening one-sided swelling, needs advice from the treating team. Swelling may become more noticeable during the early recovery period before it gradually settles, but its timing depends on the operation.
Do not add an antibiotic, steroid or extra pain medicine without checking. Some over-the-counter products contain the same active ingredient as a prescribed medicine, so combining them can lead to an unintended dose. If pain relief is inadequate or a medicine causes problems, contact the clinic so that the plan can be reviewed rather than improvising a replacement.
Food and fluids during recovery
Food needs to suit any chewing restriction while still providing enough energy and protein. A liquid or soft diet may be advised for a period before a gradual return to ordinary textures. The steps depend on the surgical site and healing, so a friend’s diet after another operation may not be suitable for you.
Very hot drinks, crunchy or spicy foods and using a straw may be unsuitable after some oral procedures. Follow your own instructions about these details. Let the team know if swallowing is difficult, nausea continues or you cannot take enough fluid. Explain dietary needs or a medical condition that affects eating before surgery so that the plan is practical for you.
Looking after the mouth and surgical site
Keeping the mouth clean helps reduce the burden of bacteria, but brushing and rinsing must be adapted to the incision and sutures. Water pressure, mouthwash or touching the wound can be inappropriate at some stages. Follow the timing and method on your discharge instructions instead of beginning an internet routine immediately after surgery.
Dissolving stitches do not necessarily mean that no follow-up is needed. Ask what the wound should look like, how to clean around it and when the team expects to review it. Avoid pulling at sutures or trying to adjust a dressing yourself. If something feels loose or looks different from the explanation you received, ask the treating team what to do.
Returning to work, driving and exercise
Returning to normal activity depends on more than pain. Sleep quality, concentration, medicines, the risk of a knock to the face and the demands of your work all matter. Desk work is different from heavy physical work or contact sport. Plan a range rather than a fixed promise and allow some flexibility if recovery takes longer than expected.
Driving requires appropriate alertness and consideration of any medicines that cause drowsiness. Ask the team when it is suitable for you. Swelling or bruising may remain visible when you return to social activities. Choosing surgery immediately before a major event can put pressure on you to rush recovery or disguise symptoms that deserve attention.
Follow-up is part of the treatment
Follow-up visits are not only for looking at the final shape. The team may assess wound healing, infection, sensation, movement, the bite or the stability of the treated structure. Advice about diet and activity can change as healing progresses. Keep the appointments even if the early appearance seems satisfactory.
If you live far away, discuss how long to remain near the treating centre and where you would be examined if a problem arose after returning home. Photographs and video calls can support selected follow-up tasks, but they cannot replace every physical examination. Have the contact details and the next appointment date before you leave the centre.
Risks and limitations without unrealistic promises
A list of possible complications does not mean they will all happen. Individual risk depends on the operation, anatomy, general health, treatment setting and the recovery plan. Informed consent means having enough time to ask about significant risks, how they might be recognised and what would be done if they occurred.
No operation guarantees perfect symmetry or removes every chance of further treatment. Living tissue heals, forms scars and changes over time. If a small correction is being considered, the right time to decide often comes after the initial healing phase, unless there is an urgent medical problem. Before-and-after photographs alone are not a complete measure of treatment quality.
Risks to discuss for this treatment
Possible risks include pain, bleeding, infection, swelling, dry socket after an extraction, injury to adjacent teeth, altered sensation and sinus-related problems where relevant to the anatomy.
When to contact the team promptly
Follow your discharge instructions for urgent contact. Important concerns include difficulty breathing, uncontrolled bleeding, rapidly worsening swelling, fever, offensive discharge, severe or increasing pain, persistent vomiting or inability to drink. Sudden changes in vision, alertness, movement or sensation also require prompt assessment.
Do not dismiss a concerning symptom simply because discomfort is common after surgery. Equally, an online photograph cannot reliably tell whether a wound is infected or whether a change is normal. Explain what has changed, when it started and any accompanying symptoms. For breathing difficulty or another emergency, seek emergency care rather than waiting for a routine message response.
What a natural result means
A natural-looking result is considered in the context of the whole face, not one feature viewed in isolation. Function, tissue support, facial proportions and the person’s own priorities matter together. Removing more tissue or making a more dramatic change is not automatically the best way to create balance.
Before surgery, agree on the change you are actually seeking and the limitations of the proposed approach. Results should be assessed at a suitable stage of healing, with comparable views where photographs are used. Early swelling can hide or exaggerate differences. Try to separate an agreed treatment goal from the pressure to match an edited social-media image.
Understanding a cost estimate
A meaningful estimate follows the assessment and a clear description of the procedure. Costs may involve the surgeon, anaesthesia, treatment facility, tests, imaging and any equipment or implants. Ask whether the quoted amount includes routine follow-up, medicines or other expected expenses. A single headline price may not describe the whole course of care.
If additional treatment or a revision became necessary, ask how that situation would be handled. Compare what is included and the reasons for the plan rather than selecting a procedure on price alone. A discount or a limited booking window should not replace time to understand the options, the recovery arrangements and the qualifications of the treating team.

Preparing your home for recovery
Before the operation, organise a comfortable sleeping space, suitable food, the recommended hygiene supplies and easy access to contact numbers. Arrange reliable help for the first days if advised. If children, an older relative or a pet depend on you, plan assistance so that you do not have to lift or resume demanding tasks too soon.
Comfortable clothing, a clean towel and a folder for prescriptions and discharge papers can be useful. Buy the supplies your team recommends rather than an elaborate collection promoted online. A simple written medicine schedule can help prevent missed or repeated doses. Keep the information somewhere that your helper can find it if you need support.
Sleep, rest and tiredness
Sleep may be interrupted in the first nights by swelling, congestion, a different head position or worry. Follow the advice for your procedure and ask if the recommended position is uncomfortable. Support should be practical, not an improvised arrangement that causes neck pain. If you use a device for sleep apnoea, discuss how it should be managed after surgery before the operation takes place.
Tiredness can follow anaesthesia and reduced food intake, but the overall course should be discussed with the team. Break tasks into manageable periods, maintain fluids as advised and return to activity gradually. Do not attribute severe drowsiness, confusion, increasing weakness or breathlessness to ordinary fatigue without seeking medical advice.
Taking medicines safely
Read the medicine name, dose and interval from your prescription. If a dose is missed, do not automatically double the next one. Antibiotics should be taken only when prescribed and according to that plan. Tell the team about a rash or other suspected reaction; swelling of the lips or tongue and breathing difficulty require urgent action.
Nausea, constipation, sleepiness or stomach discomfort may be related to a medicine. Reporting these problems allows the prescription to be reviewed if necessary. Herbal supplements and apparently simple non-prescription products can also matter around surgery. Keep an accurate list of everything you take and show it at each relevant appointment.
Travelling from another city or country
Plan more than the day of surgery. An in-person examination, additional tests or a change in the proposed approach may be needed before treatment. After surgery, remain close to the treating centre for the period the surgeon recommends. A non-changeable ticket and an early departure can create pressure to leave before the planned review.
Ask about your companion’s arrangements, the first follow-up visit, flights, long drives and lifting luggage. Carry your prescription, a treatment summary and contact details when appropriate. Before returning home, clarify how a local clinician could contact the original team if you needed an examination. Remote follow-up is useful in selected circumstances, but it cannot diagnose every complication.
Privacy and clinical photographs
Clinical photographs can be valuable for planning and follow-up. Public or educational use is a separate matter and should be discussed clearly. Before agreeing to publication, ask where an image may appear, whether you will be identifiable and how to change your preference for future use. Consent to an operation is not automatically consent to advertising.
When sending images, use the contact channel identified by the clinic and avoid including unnecessary personal information. Consistent lighting and position are more helpful for assessment than filters or retouching. An image from a previous case can support a discussion, but it does not guarantee that another person will heal or look the same way.
When a second opinion can help
For elective surgery, particularly a complex, costly or multi-stage proposal, a second opinion can help clarify the decision. Bring the complete records and ask the second clinician to explain the diagnosis and options independently. Different recommendations are not always evidence of an error; sometimes they reflect reasonable approaches with different priorities.
If the diagnoses differ substantially, ask what findings support each conclusion. The aim is to understand the choice, not to collect a series of short price quotations. Keep your records and give yourself time to think. Feeling uncertain is a reason to ask more questions, rather than agreeing because of a deadline or pressure to make a booking.
Revision surgery needs a specific plan
A revision does not always mean that an earlier treatment failed completely. There may be a small residual concern after healing, a complication or a more substantial dissatisfaction. Before deciding, the surgeon needs to understand the previous procedure, the time since treatment, available images and the current condition of the tissues.
Scar tissue or altered bone can make another operation more complex. The timing depends on the problem: an urgent medical issue may need early care, whereas an aesthetic judgement often needs time for swelling and tissues to settle. Describe the specific concern and the improvement you hope to achieve. Repeated operations should not become a search for an unattainable perfect image.
A personal plan is different from a general guide
Online information describes common patterns. Your instructions depend on age, health, work, travel distance, the extent of the procedure and the response in the first days. Two people undergoing an operation with the same name may receive different dietary or exercise advice. That difference can be appropriate and is not a reason to substitute another person’s instructions for your own.
A good plan also needs to be workable. If a medicine is unavailable, a diet conflicts with another condition or you cannot attend a proposed visit, say so before surgery. The team may be able to suggest a practical alternative. Hiding a difficulty does not remove it; it can make an already demanding recovery period harder to manage.
Deciding whether this is the right time
Elective treatment should fit a considered decision, not a moment of pressure. Discuss concerns about your appearance openly, including any outside pressure or expectation that surgery will solve unrelated problems. The conversation is intended to align what you hope for with what treatment can realistically offer.
Sometimes allowing more time, postponing an operation or obtaining an independent opinion improves the decision. You should be able to explain why you want the change, understand the likely recovery and accept the main limitations. If those points are still unclear, another conversation is more useful than rushing to choose a date.
Common questions before deciding
Does everyone who asks about this procedure need an operation? No. The examination may point towards observation, a non-surgical treatment or no intervention. It may also identify a different problem from the one you initially suspected. A useful consultation explains that distinction and the reasons for the recommendation. It should leave you better informed even if you decide not to proceed.
Can I choose my treatment from a before-and-after photograph? A photograph is one piece of information, not a complete assessment. It does not show the whole medical history, the examination, every view or every stage of healing. Ask what makes the example relevant to your anatomy and where the comparison stops being useful. Similar-looking concerns may need different approaches.
What if I am not ready to make a decision at the first visit? Take time to review the explanation and write down remaining questions. Elective surgery should follow an informed choice. If you are unsure about the purpose of a movement, the extent of a change or the practical arrangements for recovery, another discussion is more useful than making an uncertain commitment.
Can several facial procedures be combined? A combined plan is considered only after the relationship between the concerns has been assessed. More treatment is not automatically better. Ask what each component adds, how it changes the anaesthesia and recovery, and whether doing things separately is an option. The proposal should have a clear reason for each part.
How should I explain dissatisfaction after treatment? Describe the specific issue, when you noticed it and whether it is changing. Distinguish pain or a functional difficulty from a concern about the early appearance. The treating team can assess it in the context of healing. Do not delay reporting an urgent symptom while waiting for a routine cosmetic review.
What information should be written down before I go home? Keep the medicine instructions, wound-care advice, food and activity restrictions, the date of the next visit and the appropriate contact number. Make sure you understand when to call urgently and which service to use outside clinic hours. Ask your companion to hear the instructions too if that would help.
Will my plan be the same as someone else’s? Not necessarily. The extent of the procedure, health conditions, previous treatment and response during recovery can all affect instructions. Do not change your own plan because another patient returned to exercise or eating sooner. If the difference worries you, ask the team to explain the reason for your restrictions.
Where can I read more before the appointment? The related articles below provide background on the topic, while the professional patient-information links offer another starting point. Keep the questions that arise as you read. The purpose is to prepare a better conversation about your own situation, rather than to diagnose yourself from a general description.
Questions to take to your appointment
Ask what is causing the concern, whether it needs treatment and which options are suitable. Ask what the proposed operation can change, what it cannot change, and which structures are relevant to the risks. You can also ask how the recommendation would differ if you chose to wait.
Discuss anaesthesia, the treatment setting, support at home, time away from work, food and oral hygiene, the first follow-up visit and the symptoms that need urgent contact. Ask for a written estimate and clear instructions. These practical questions help turn a general explanation into a plan you can follow.
Read related English articles or contact the clinic to arrange a consultation.
Further reading
Questions about Oral & dental surgery?
An examination helps identify what is relevant to your situation. Ask about suitable options, their limitations, recovery and follow-up before deciding.
Contact the clinic →